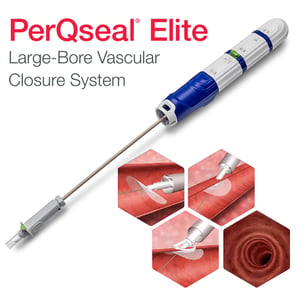
One device and done. Over-the-wire delivery with no preclose or preprocedural steps. Deploy at the end of the primary procedure. Leave nothing permanent behind. 0% major complications per VARC-3.1
Confirm before you commit.
Repositionable and recoverable.* Maintain wire access until hemostasis is verified, prior to implant release.
Near-instant hemostasis. Mean time to achieve hemostasis is < 1 minute.1
Respect the vessel.
Patch, don’t pinch. Close with no sutures, no purse-string effect.
100% bioabsorbable. Leave nothing permanent behind. Vessel expected to return to its natural state within ~180 days.
Consistent control. Uniform stability through every TAVR twist and turn. From sheath insertion through valve delivery.
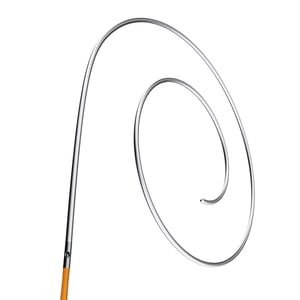
Pre-formed spiral tip. Designed for reliable ventricular positioning, dependable contact, superior tip retention and controlled tip load.
280 cm length. Stays in-hand throughout deployment. Designed to support continuous procedural control, increased control for taller patients, and backup pacing after valve placement.
Cleared to pace.
On label, on purpose. FDA-cleared for temporary intracardiac pacing. Designed and labeled for LV use.
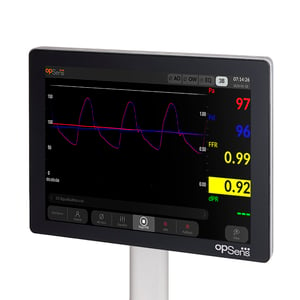
No kitting. Valve delivery and pacing combine in one wire. No need for a separate pacing catheter, venous access or disposable pacing kit.
Don’t scrape by. PTFE-sleeved shaft, low-resistance design, and defined pacing zones that deliver current directly to the ventricle — no manual workarounds required.
Contact us about Haemonetics Interventional Technologies.
* Repositionable and recoverable prior to implant release
† Major venous access site closure-related complications through 30-day follow up
‡ In Per Protocol population (N=66)
§ Minor venous access site closure-related complications through 30-day follow up
1. Results from the prospective, single-arm, multi-center ELITE arterial study; VARC-3 major device-related vascular access site complications (adjudicated) through 30 days. See PerQseal® Elite instructions for use (DP4-C56-5). 2. VASCADE MVP IFU 3972. 3. Compared to Manual Compression. Natale A, et al. Venous vascular closure system versus manual compression following multiple access electrophysiology procedures: The AMBULATE Trial. JACC Clin Electrophysiol October 2019. DOI: 10.1016/j.jacep.2019.08.013. 4. Al-Ahmad A, et al. Results from the prospective, multicenter AMBULATE-CAP trial: Reduced use of urinary catheters and protamine with hemostasis via the mid-bore venous vascular closure system (Vascade MVP) following multi-access cardiac ablation procedures. J Cardiovasc Electrophysiol Dec 2020. https://doi.org/10.1111/jce.14828. NCT03573206. 5. AMBULATE Same Day Discharge Registry Retrospective Study: NCT04538781. 6-7. Eldadah ZA, et al. Same-day discharge following catheter ablation and venous closure with VASCADE MVP: A post-market registry. J Cardioavasc Electrophsyiol 2022. https://doi.org/10.1111/jce.15763 NCT04203329. 8. VASCADE MVP XL IFU 4911.



















 Interventional Technologies